



Medically reviewed by Shaun Larsen, OD – Doctor of Optometry, Southern College of Optometry. Low vision rehabilitation and contact lens specialist.
Last clinically reviewed: July 2026 | Next scheduled review: July 2027
In brief: 20/60 means that at 20 feet you resolve detail that a person with reference-standard vision resolves at 60 feet. Under the WHO ICD-11 classification, 20/60 sits in the mild vision impairment band. It is below the 20/40 threshold that most US states require for an unrestricted driving licence, but it is well above the 20/200 threshold for legal blindness. Whether 20/60 is a minor inconvenience or a significant disability depends almost entirely on why it is 20/60 – which is what the rest of this article is about.
What the two numbers actually mean
“20/20” is a word that almost everyone is familiar with. Many individuals consider it a source of pride. “I have 20/20 eyesight, according to my doctor.” If your vision is less than 20/20, such as 20/200, on the other hand, maybe a source of tremendous stress and anxiety. I’ll explain what these phrases truly imply in this discussion.
The notation is a Snellen fraction, and it is not a measure of how much vision you have as a percentage. The numerator is the testing distance in feet. The denominator is the distance at which a reference observer resolves the same detail. So the fraction is a ratio of distances, not a proportion of normal sight – 20/40 does not mean "half of normal vision".
Assume you have two persons, one with 20/20 vision and the other with 20/60 vision. The 20/60 line is the smallest line of letters that the second person can see at a distance of 20 feet. The first person with “normal” 20/20 vision, might see the identical line from 60 feet away. The 20/60 letters are 3 times the size of the 20/20 letters, thus someone with normal vision may see a 20/60 letter from 3x’s the distance as someone with 20/60 vision.
The geometry underneath it. Snellen optotypes are constructed on a 5×5 grid in which each stroke and each gap subtends 1 minute of arc at the design distance, and the whole letter subtends 5 minutes of arc. One arcminute of stroke width is roughly the resolution limit set by foveal cone spacing in a healthy eye. So 20/20 is not an average or an aspiration – it is approximately the physical sampling limit of the human retina. This is also why better-than-20/20 results are unremarkable: many healthy young adults read 20/15, and 20/20 is better understood as a reference standard than as a ceiling.
A 20/60 letter is three times the linear dimension of a 20/20 letter, and therefore nine times the area. That difference in area, rather than the ratio of 3, is closer to what determines how much magnification a person needs to read comfortably.
Snellen, logMAR and why clinicians increasingly use the latter
The Snellen chart has real measurement weaknesses that matter when acuity is being tracked over time: the number of letters per line is unequal, the size progression between lines is irregular, letter spacing varies, and the legibility of individual letters differs. A change from 20/40 to 20/50 is therefore not a fixed, comparable step.
The ETDRS (Early Treatment Diabetic Retinopathy Study) chart was designed to fix this. It uses five equally legible Sloan letters per line, equal spacing proportional to letter size, and a constant 0.1 log-unit size progression between lines. Acuity is then expressed in logMAR – the base-10 logarithm of the minimum angle of resolution:
20/20 = 0.0 logMAR
20/40 = 0.3 logMAR
20/60 = 0.5 logMAR
20/70 ≈ 0.54 logMAR
20/200 = 1.0 logMAR
20/400 = 1.3 logMAR
Because each line is worth exactly 0.1 logMAR and each letter 0.02, change can be quantified as "gained 8 letters" or "lost 2 lines" – which is why every major ophthalmic clinical trial reports outcomes in ETDRS letters rather than Snellen fractions. If you are being monitored for a retinal condition and want to know whether treatment is working, logMAR or letter scores are the meaningful number to ask for.
Where 20/60 sits in the official classifications
WHO ICD-11 distance vision impairment categories (based on presenting visual acuity in the better eye):
No impairment: 20/40 or better
Mild impairment: worse than 20/40 to 20/70 – 20/60 falls here
Moderate impairment: worse than 20/70 to 20/200
Severe impairment: worse than 20/200 to 20/400
Blindness: worse than 20/400, or visual field constricted to under 10 degrees
US legal blindness is a statutory and benefits definition, not a WHO one: best-corrected visual acuity of 20/200 or worse in the better eye, or a visual field of 20 degrees or less in the better eye. 20/60 does not approach this threshold.
20/60 Vision can be considered visually impaired

A person is legally blind in the United States when best-corrected acuity in the better eye is 20/200 or worse, or when the visual field in the better eye is restricted to 20 degrees or less. The distinction matters: at exactly 20/200 a person does qualify. Even if a person is legally blind, some vision may be beneficial and helpful in daily life.
All of these classifications are applied to presenting or best-corrected acuity – that is, acuity measured with whatever correction you normally wear, or with the best correction achievable. Uncorrected acuity is not the basis for any of them. Someone who is −4.00 D myopic and sees 20/400 without glasses but 20/20 with them is not visually impaired; they are short-sighted. Visual impairment can also be determined by poor night vision, minimal side vision, double vision, and vision loss in one eye.
Low vision is a phrase used to describe the vision that is below normal (20/70 or worse) that cannot be corrected with regular glasses. Blindness is not the same as low vision. Low-vision individuals may make use of their eyesight. Low eyesight, on the other hand, might make it difficult to conduct everyday tasks like reading or driving. However, regardless of the exact acuity, someone has low vision if their diminished eyesight hinders their regular activities.
That last sentence is the important one, and it deserves more weight than the numbers above it. "Low vision" is a functional category, not a threshold. Clinically it describes vision that cannot be fully corrected by spectacles, contact lenses, medication or surgery, and that interferes with everyday activity. A patient at 20/60 with dense central scotoma and poor contrast sensitivity has low vision in every sense that matters and will benefit from rehabilitation; a patient at 20/80 from an uncorrected refractive error does not have low vision at all, because refraction fixes it.
Visual impairment is defined as diminished vision that cannot be corrected. Uncorrectable vision refers to vision that cannot be corrected further using eyeglasses or contact lenses; it does not refer to vision without glasses.
Visual impairments come in a variety of shapes and sizes, with varied degrees of severity. Visual acuity isn’t a good indicator of a person’s vision issues on its own. Someone with moderate 20/60 vision may have trouble functioning, but someone with poor acuity (20/200) may not have any issues with everyday tasks.
Why acuity alone is a poor description of vision
Snellen acuity measures one narrow thing: the smallest high-contrast black letter you can identify on a bright white chart at distance, under controlled lighting, with unlimited time. Real visual function depends on several other measurable dimensions, and two people who both test 20/60 can have entirely different levels of disability.
Contrast sensitivity. The real world is mostly low-contrast – a kerb, a step edge, a face, a grey car in rain. Contrast sensitivity loss is the strongest visual predictor of mobility difficulty, falls, and driving problems, and it can be substantially reduced while acuity remains near normal. Cataract, AMD, glaucoma and optic neuropathy all degrade contrast disproportionately. The Pelli–Robson chart measures it in a few minutes and is almost never done in a routine eye examination. Ask for it.
Visual field. Advanced glaucoma or retinitis pigmentosa can leave 20/20 central acuity inside a field so constricted the person cannot cross a road safely – and can meet the legal blindness definition on field criteria alone while reading the bottom of the chart.
Scotoma location. In macular disease, whether the blind spot sits directly on fixation or just off it changes reading ability far more than the acuity figure suggests. Microperimetry maps this; acuity does not.
Glare and light adaptation. Cataract and corneal disease scatter light forward, so acuity measured in a dim lane can be dramatically better than function in sunlight or against oncoming headlights.
Binocularity and ocular motility. Diplopia or loss of stereopsis affects depth judgement and driving independently of acuity in either eye.
Reading speed. For most patients the practical question is reading, and reading speed under standardised conditions (MNREAD or Radner charts) correlates with day-to-day capability far better than distance acuity.
This is why a 20/60 result should be treated as the beginning of an assessment, not the conclusion of one.
How is 20/60 Vision measured?
The Snellen acuity chart is the traditional chart of large and small letters, referred to as “optotypes” in this context. The chart is made up of 11 lines of block letters, with the top row starting with a huge single letter. As you go from top to bottom, the number of letters on each row increases. The letters gradually shrink in size, providing for more letters on each succeeding line.
When assessing visual acuity, the patient closes an eye and reads the letters on the chart from top to bottom, starting at the top and working down. Visual acuity in the uncovered eye is determined by the lowest row of letters that the patient correctly reads. The test is performed with the opposite eye, and then both eyes at the same time.
Test conditions are part of the measurement. Reproducible acuity requires a standardised testing distance (20 feet, or an optically equivalent shorter lane using mirrors), chart luminance in the region of 85–300 cd/m², correct occlusion of the untested eye rather than a hand pressed against it, and a defined scoring rule – commonly, the line is credited when the majority of its letters are read correctly, with partial credit noted as, for example, 20/60−2. Acuity taken on a phone app at arm’s length under a ceiling light is not comparable to a clinical measurement and should not be used to make decisions.
The quality of your vision will be determined by the results of your acuity test (chart reading). The findings of your eyesight (acuity) will be presented as a fraction. Each row has fractions to the left of it that indicate how well that you see.
If you are able to get the letters to the fifth line, for instance, your vision would be described as 20/40; if you could read all the way to the seventh line, it would be described as 20/25. Consider the figures in feet while interpreting your reading. A person with 20/60 vision, for example, can read at 20 feet what someone with normal vision might see at 60 feet.
To drive a vehicle in the United States without corrective glasses, you must have a vision score of 20/40 or above. Visual acuity of 20/200 (or worse) qualifies someone as legally blind.
20/10 – When the second number decreases, it means you have superior to average vision. You can see well at 20 feet away what a person with “normal” vision can see from 10 feet away while using an eye chart.
Can a prescription be estimated from acuity?
Based on your glasses prescription, eye physicians can typically predict what your uncorrected VA will be. This is most effective for nearsightedness. In other words, for every half step up in glasses prescription (i.e. -1.00 vs. -1.50), one can see one less line on an acuity chart.
A prescription of – 1.00 equals 20/40 vision, -1.50 equals 20/50 vision, and so on. This chairside approximation is sometimes called Egger’s rule: roughly each Snellen line lost from 20/20 corresponds to about −0.25 D of simple myopia. On that basis 20/60 corresponds to approximately −0.75 to −1.00 D, and 20/200 to roughly −2.50 to −3.00 D.
Treat this only as triage. It holds only for reasonably pure myopia in an eye with clear media and a healthy retina. It fails in the presence of astigmatism (which adds blur not captured by the spherical value), cataract or other media opacity, and macular or optic nerve disease – any of which can reduce acuity to 20/200 with no significant refractive error at all. It cannot be used in reverse to diagnose anything, and it does not apply to hyperopia at all.
Anyone with an anatomically healthy eye, that is, one that is free of illness, should be able to correct their vision to 20/20 using glasses or contact lenses. It’s worth noting, though, that a person’s best-corrected acuity may not be 20/20 but have no visible evidence of illness on rare occasions. Amblyopia is the usual explanation – a developmental reduction in acuity arising from unequal refractive error, strabismus or media obstruction during the critical period of visual development, which leaves a structurally normal-looking eye that never achieves full acuity.
Farsightedness is more difficult to assess since it is influenced by a variety of other variables, such as age and concentrating ability. A young hyperope can accommodate through several dioptres of latent hyperopia and still read 20/20, so uncorrected acuity says almost nothing about the magnitude of the error. This is why cycloplegic refraction – temporarily paralysing accommodation with drops – is used in children and young adults.
Even with 20/20 vision, you should get your eyes tested on a regular basis to ensure that your acuity and eyesight remain as good as possible for as long as feasible. Because there are various variables that contribute to vision difficulties, frequent eye examinations may discover possible problems early and, if necessary, cure them before they worsen.
Conditions that can result in 20/60 vision

The single most useful question about a 20/60 result is whether it is refractive – correctable with lenses – or pathological. That distinction determines everything that follows: prognosis, treatment, driving eligibility, and whether low vision rehabilitation is relevant. Globally, uncorrected refractive error remains the largest single cause of vision impairment, and it is the one that is trivially fixable.
Myopia is another term for nearsightedness. When a person is near to an item, they can see it clearly, whereas things at a distance look blurry. Nearsightedness affects roughly 30% of the population and may be readily be corrected with contact lenses or glasses. The light entering an over-long eye focuses in front of the retina. Prevalence is rising sharply worldwide, particularly in East Asia, and high myopia carries elevated lifetime risk of retinal detachment, myopic maculopathy, glaucoma and cataract – so a high prescription is a reason for surveillance, not merely stronger lenses.
Farsightedness, sometimes called hyperopia, is the polar opposite of nearsightedness. Items that are far away can be seen clearly, while objects that are near to them are hazy. Like myopia, this is also readily curable.
Astigmatism is a condition in which the surface of the cornea or lens is not spherical, leading your eyes to focus on two spots rather than one. This may result in eye strain, soreness, headaches, blurred/distorted vision, and night vision issues, among other things. Astigmatism is readily treated with the right contacts or eyeglasses. Regular astigmatism is correctable with a cylindrical lens. Irregular astigmatism – as in keratoconus, corneal scarring or post-surgical ectasia – is not, because the surface distortion is not a smooth toric shape; those eyes require rigid or scleral contact lenses to neutralise the aberration.
Presbyopia is a condition in which your eye’s lens changes and becomes less flexible, this makes it harder to focus on close objects. This may happen between the ages of 40 and 60. There are numerous visual changes between the ages of 40 and 60, but they grow more severe beyond that. Note that presbyopia affects near vision only and does not produce a 20/60 distance result; if distance acuity is reduced, presbyopia is not the explanation.
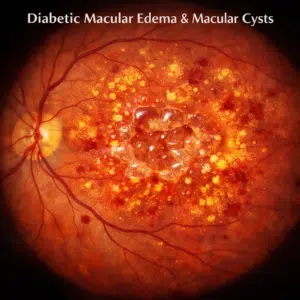
People with diabetes may notice changes in their eyesight and/or visual functionality on a daily basis as a result of the condition. Diabetic retinopathy is a condition in which the blood vessels that supply the retina acquire small, irregular branches that leak. This may cause visual problems and, over time, may cause serious retinal damage. Although laser techniques and surgical therapies may slow the growth of diabetic retinopathy, the most crucial step in treating it is to control blood sugar. Two additions worth knowing: intravitreal anti-VEGF injection, not laser, is now first-line treatment for centre-involving diabetic macular oedema; and short-term blurring that fluctuates with blood glucose is a separate phenomenon caused by osmotic swelling of the lens, which is reversible and is not retinopathy.
The optic nerve is damaged by glaucoma. This is most usually caused by an increase in internal pressure in the eye as a result of issues with fluid flow or drainage inside the eye. It may also happen when the intra-ocular or internal pressure of the eye does not rise (normal-tension glaucoma), but the optic nerve does not get adequate blood flow. The most common kind of glaucoma has no early symptoms but impairs side (peripheral) vision and trouble with night vision are the earliest evidence of damage. It may be treated with medications or, in certain cases, surgery to reduce vision loss if detected early. Glaucoma characteristically spares central acuity until late, so a person with 20/20 acuity can have advanced glaucomatous field loss – and, conversely, glaucoma is rarely the explanation for an isolated 20/60 reading.
A cataract is a clouding of the lens within the eye, which may affect one or both eyes. The clouding prevents light from reaching the retina in the rear of the eye, leading to vision loss. Aging, long-term exposure to UV radiation from the sun, injury, sickness, and hereditary problems are all possible causes. A cataract may be surgically removed if the eye is healthy. The eye is usually implanted with an intraocular lens implant, and vision is restored. In otherwise healthy eyes, cataract surgery has a high success rate. Cataract surgery, on the other hand, is not always feasible for patients who have other eye disorders. To make the most of their residual eyesight, these folks may need low-vision rehabilitation. Cataract is one of the most common causes of a 20/60 result in adults over 60, and it is the most reversible – which is exactly why a new 20/60 finding should be examined rather than assumed to be permanent.
Macular Degeneration is a degeneration of the central section of your retina, which is the region in the back of your eye that receives visual images and conveys them to the brain. A gray/black dot will appear in the middle of a person’s vision, which will progressively become bigger. This illness is the most common cause of eyesight loss and is irreversible; however, treatment can slow progression, and in neovascular (wet) AMD intravitreal anti-VEGF therapy frequently stabilises or improves acuity.
Also worth ruling out at 20/60: amblyopia (long-standing and usually detected in childhood), corneal disease including keratoconus and dystrophy, retinal vein occlusion, epiretinal membrane and macular hole, optic neuropathy, and – particularly where the reduction is sudden or affects one eye – neurological causes requiring prompt investigation. A newly discovered 20/60, especially if it is sudden, one-sided, or accompanied by distortion, pain, flashes or floaters, warrants examination rather than a new spectacle prescription.
Workplace eye injuries are rather prevalent. According to the National Institute for Occupational Safety and Health (NIOSH), around 2,000 employees in the United States suffer work-related eye injuries that need medical attention every day. However, eye specialists and safety experts think that proper eye protection may reduce the severity of or even avoid 90% of these accidents.
What can you do if you have uncorrectable 20/60 vision?
To drive a vehicle in the United States without corrective glasses, you must have a visual acuity of 20/40 or above. Visual acuity of 20/200 (or worse) qualifies someone as legally blind. Therefore with 20/60 vision, you will either need a visual aid to get your vision to 20/40 or your license will be restricted.
Driving standards are set state by state, and the detail matters. Most states require 20/40 or better in at least one eye, with correction if needed, for an unrestricted licence. Many issue restricted licences at acuities between roughly 20/50 and 20/70 – typical restrictions being daylight only, no interstate driving, or a defined radius from home. Visual field requirements apply independently, commonly in the region of 110–140 degrees horizontally, and a driver can fail on field while passing on acuity. Commercial licensing under federal rules is stricter. Check your own state licensing authority’s current published standard before assuming anything about your eligibility.
Bioptic telescope driving. A majority of US states permit driving with a bioptic telescope system – a small telescope mounted in the upper portion of a spectacle lens, used with a brief glance for road signs and signals while the carrier lens provides the wide field for general driving. Eligibility criteria, required training hours and the acuity thresholds through the carrier and telescope differ substantially between states, and licensing typically requires a formal training and on-road assessment programme. For drivers at 20/60 to 20/100 from stable central vision loss, this is often the difference between driving and not driving, and it is under-known.
For persons who have lost their eyesight, low vision rehabilitation is the gold standard of therapy. If you or someone you know has a vision problem, speak with your optometrist about low vision treatment. Low vision therapies provided by an optometrist may assist persons with low vision to reclaim their independence and enhance their quality of life.
What a low vision assessment actually involves – and how it differs from a routine eye exam. A routine examination asks whether the eye is healthy and what lens correction it needs. A low vision assessment asks what you are unable to do and engineers a solution. It typically includes acuity measured at working distance on a low vision chart, contrast sensitivity, visual field and scotoma mapping, glare testing, and a structured discussion of specific goals – reading a medication label, seeing a laptop, recognising faces, continuing a hobby.
From that, magnification is calculated rather than guessed, using the ratio between the print size you need and the print size you can currently resolve. Interventions include high-add reading spectacles and prismatic half-eyes, hand and stand magnifiers, telescopes for distance tasks, electronic video magnifiers and portable CCTVs, head-mounted electronic systems, screen readers and OCR software, non-optical measures such as task lighting and high-contrast marking, and – for people with central scotoma – eccentric viewing and steady-eye training, which teaches the use of a preferred retinal locus outside the damaged fovea. That training alone can transform reading ability without any change in measured acuity.
People with impaired vision may acquire a multitude of ways to assist them to carry out everyday tasks with the vision they have left. Educational and vocational counseling, low vision occupational therapy, rehab training, and other services are available via government and commercial programs.
If you have best-corrected 20/60 vision or you’re struggling to do your daily activities efficiently call one of our low vision specialists that are near you for an appointment.
FAQs
Is 20/60 vision OK for driving?
Generally, no – not for an unrestricted licence. Most US states require 20/40 or better, with correction, in at least one eye. At 20/60 you would typically need either correction that brings you to 20/40, a restricted licence (commonly daylight-only), or a bioptic telescope programme where your state permits it. Standards vary by state and by licence class, so verify with your own licensing authority. But it’s important to keep in mind that driving is a difficult endeavor that calls for more than simply sharp vision. Here are a few things to think about:
Legal Requirements: Depending on the locality and the type of license (such as an ordinary driver’s license, a commercial driver’s license, etc.), different visual acuities may be needed to obtain a driver’s license. The specific rules in your local jurisdiction should be checked because they may be different.
Peripheral Vision: For safe driving, having adequate peripheral vision is crucial. Reduced peripheral vision might make it more difficult for you to see other cars, people walking nearby, and other nearby objects. This might be crucial to visual acuity.
Night Vision: Some people may have good daytime visual acuity but have trouble seeing well at night. Driving at night or in low light might be particularly challenging in this situation. This is usually a contrast sensitivity and glare problem rather than an acuity problem, and it is the reason many restricted licences are daylight-only.
Depth perception is essential for determining the distance between your car and other roadside items. Your ability to drive safely may be impacted by problems with depth perception.
If your vision can be corrected with glasses or contact lenses to 20/20, you should wear corrective lenses. Where a licence carries a corrective-lens restriction, driving without them is a licence violation.
How common is 20/60 vision?
Depending on the population and age group under consideration, the prevalence of 20/60 vision can change dramatically. Typically, 20/60 vision is regarded as a degree of visual acuity that, for some people, may necessitate the use of corrective lenses in order to meet the requirements for unrestricted driving.
The distinction that matters here is between presenting acuity (what you see with whatever you currently wear) and best-corrected acuity (the best achievable). Presenting acuity around 20/60 is common, and the great majority of it is uncorrected or under-corrected refractive error – which is why uncorrected refractive error is the leading cause of vision impairment worldwide and why it is also the most easily reversed. Best-corrected 20/60 is considerably less common and almost always indicates ocular pathology, with prevalence rising steeply with age.
Here are a few broad observations regarding the predominance of 20/60 vision:
Age-Related Changes: People’s vision may inevitably get worse as they get older. Presbyopia, which causes difficulties focusing on close objects, can become increasingly prevalent in middle-aged and older people, potentially resulting in vision as poor as 20/60 or worse without corrective lenses.
Myopia and Hyperopia: If refractive problems like myopia (nearsightedness) and hyperopia (farsightedness) are not treated with glasses or contact lenses, they can result in vision of 20/60 or worse. These disorders are quite prevalent, with age and geographic differences in occurrence.
Other Eye problems: As people age, other eye problems like cataracts, glaucoma, and macular degeneration become more common and can also impact visual acuity.
With the aid of corrective lenses, such as glasses or contact lenses, many people with refractive problems can attain 20/20 vision or better.
What’s the worst eyesight you can have to drive?
The worst eyesight you can have to legally drive varies by country and region, as different places have their own regulations and requirements for obtaining a driver’s license. These requirements typically consider both visual acuity (clarity of vision) and visual field (peripheral vision).
In practical US terms: 20/40 is the usual threshold for an unrestricted licence; many states permit restricted licences down to somewhere between 20/50 and 20/70; and states operating bioptic programmes may license drivers with carrier-lens acuity as low as 20/200 subject to telescope-corrected acuity, field requirements, training and on-road assessment. Field standards apply independently of acuity.
What prescription is 20/60?
There is no fixed answer, because acuity and refractive error are not in a fixed relationship. Using the same rule of thumb applied earlier in this article (approximately one Snellen line per 0.25 D of simple myopia), 20/60 corresponds to roughly −0.75 to −1.00 D – not −2.00 D, which would place acuity closer to 20/100–20/200. The estimate breaks down entirely where astigmatism, cataract, or retinal or optic nerve disease is present, and it does not apply to hyperopia, where accommodation masks the error. Only a refraction can establish your prescription.
What is 20/60 in Snellen?
In Snellen notation, 20/60 vision means that a person can see at 20 feet what a person with normal vision can see at 60 feet. This indicates that the person’s vision is less sharp than someone with 20/20 vision. In Snellen eye charts, the letter sizes are calibrated to represent the size they should appear to a person with normal vision at a specified distance. Equivalent expressions: 6/18 in metric notation, 0.33 as a decimal, and 0.5 logMAR.
What is an example of 20/60 vision?
To provide an example of what someone with 20/60 vision might experience, imagine looking at an eye chart under specific conditions. In this case, someone with 20/60 vision would be able to read the same line of an eye chart at 20 feet that a person with normal 20/20 vision could read at 60 feet.
In everyday terms, someone at 20/60 will typically read large newspaper headlines but struggle with body text at normal distance; recognise a familiar person across a room by gait and posture before facial features resolve; find road signs legible only at roughly a third of the usual distance, which is the specific reason it falls short of the driving standard; and manage a television comfortably by sitting closer. Note again that these are typical experiences for a refractive 20/60 – the same acuity caused by macular disease, with a central scotoma and reduced contrast sensitivity, is functionally much more disabling.
Is 20/60 better than 20/100?
Yes, 20/60 vision is better than 20/100 vision. In the Snellen visual acuity system, the first number represents the test distance (20 feet), and the second number represents the distance at which a person with normal vision can read the same line of letters on the eye chart. The larger the second number, the poorer the acuity.
Is 20/30 vision better than 20/60?
Yes, 20/30 vision is better than 20/60 vision. In the Snellen visual acuity system, the first number represents the test distance (20 feet), and the second number represents the distance at which a person with normal vision can read the same line of letters on the eye chart.
What is 20/60 vision in meters?
In metric notation 20/60 is written 6/18, because the standard metric testing distance is 6 metres rather than 20 feet. This is the notation used across the UK, Europe, India and Australia, and it is the notation the WHO uses in the ICD-11 classification.
The direct arithmetic conversion (6.10 m and 18.29 m) is correct but is not how the notation is used in practice – 6/18 is the standard form, and 6/18 and 20/60 denote exactly the same level of acuity.
Can 20/60 vision be improved?
It depends entirely on the cause. If it is refractive, spectacles or contact lenses will usually restore it fully. If it is cataract, surgery usually restores it. If it results from retinal or optic nerve damage, the acuity itself may be permanent – but function can still be improved substantially through low vision rehabilitation, magnification, contrast and lighting management, and eccentric viewing training. The first step in every case is a dilated examination to establish which of these applies. There is no exercise, supplement or device that improves acuity in a structurally normal eye beyond what correction achieves.
Does 20/60 vision qualify for disability benefits?
Under the US Social Security Administration’s listings, statutory blindness requires best-corrected central acuity of 20/200 or worse in the better eye, or a visual field limitation as specified in the listings, so 20/60 alone does not meet that standard. Some state and local programmes, workplace accommodation provisions under the Americans with Disabilities Act, and specific service eligibility criteria use different and often lower thresholds, and accommodations are generally assessed on functional limitation rather than on an acuity figure. Verify against the specific programme.
References
1. World Health Organization. International Classification of Diseases, 11th Revision (ICD-11) – vision impairment including blindness. who.int.
2. World Health Organization. World Report on Vision. Geneva: WHO; 2019.
3. Ferris FL, Kassoff A, Bresnick GH, Bailey I. New visual acuity charts for clinical research. *Am J Ophthalmol*. 1982;94(1):91–96.
4. Bailey IL, Lovie JE. New design principles for visual acuity letter charts. *Am J Optom Physiol Opt*. 1976;53(11):740–745.
5. Pelli DG, Robson JG, Wilkins AJ. The design of a new letter chart for measuring contrast sensitivity. *Clin Vis Sci*. 1988;2:187–199.
6. Owsley C, Sloane ME. Contrast sensitivity, acuity, and the perception of “real-world” targets. *Br J Ophthalmol*. 1987;71(10):791–796.
7. Legge GE, Ross JA, Luebker A, LaMay JM. Psychophysics of reading. VIII. The Minnesota Low-Vision Reading Test. *Optom Vis Sci*. 1989;66(12):843–853.
8. American Academy of Ophthalmology. Vision Rehabilitation Preferred Practice Pattern. aao.org.
9. US Social Security Administration. Disability Evaluation Under Social Security – Section 2.00, Special Senses and Speech. ssa.gov.
10. National Highway Traffic Safety Administration / state licensing authorities. Driver vision standards vary by state – consult your state DMV for the current requirement.
11. Bowers AR, Apfelbaum DH, Peli E. Bioptic telescopes meet the needs of drivers with moderate visual acuity loss. *Invest Ophthalmol Vis Sci*. 2005;46(1):66–74.







 Shop Best Low-Vision Aids with FREE Doctor Consultation.
