



Medically reviewed by Shaun Larsen, OD, Doctor of Optometry, Southern College of Optometry.
Last clinically reviewed: July 2026 | Next scheduled review: July 2027
If your peripheral vision has changed suddenly, treat it as an emergency. Sudden loss of side vision can indicate a retinal detachment, a stroke, acute angle-closure glaucoma or giant cell arteritis, all of which cause permanent damage within hours to days if untreated. Call emergency services or go to an emergency department now if you have: a curtain or shadow moving across your vision; a sudden shower of new floaters with flashing lights; sudden loss of vision on one side in both eyes, particularly with weakness, numbness, confusion or difficulty speaking; severe eye pain with redness, haloes and nausea; or vision loss with headache, scalp tenderness or jaw pain if you are over 50. Gradual loss over months, which is the usual pattern in glaucoma and retinitis pigmentosa, needs a prompt appointment rather than emergency care, but should not be left.
Peripheral vision loss, often known as tunnel vision, can be caused by a variety of medical diseases, including stroke, glaucoma, and diabetic eye disease.
What is the peripheral vision?
Peripheral vision refers to the ability to see things that are not directly in front of you. When you see things out of the corner of your eye, you’re using peripheral vision. Rod nerve cells, which are found outside of the macula (the center of the retina), aid peripheral vision.
How far it extends. A single healthy eye sees roughly 100 degrees temporally (outward), 60 degrees nasally (toward the nose), 60 degrees upward and 70 to 75 degrees downward. The limits are partly anatomical: the nose blocks the inner field and the brow the upper. Both eyes together span about 200 degrees horizontally, with a central overlap of roughly 120 degrees that provides depth perception.
What it is good at, and what it is not. Peripheral retina is rod-dominated, so it detects motion extremely well and functions in dim light, but resolves very little detail and almost no colour. That division of labour is why a movement caught at the edge of vision makes you turn your head: the periphery detects, the fovea identifies.
Why peripheral loss is so easily missed. Two things conceal it. The fellow eye covers what the affected eye cannot see, and the brain performs perceptual filling-in, completing missing areas with surrounding pattern so convincingly that no gap is experienced. People do not see a black patch; they see nothing unusual at all, and simply bump into things or fail to notice a car. This is why field loss is usually found on examination rather than reported by the patient, and why glaucoma can destroy most of a visual field before anyone notices.
Peripheral vision is crucial because it allows you to perceive objects in your immediate surroundings without turning your head or moving your eyes. You use this for a variety of things, including driving and sports.
PVL (peripheral vision loss), often known as tunnel vision, is the loss of peripheral vision. PVL patients can see what is directly in front of them, but their side vision may be impaired.
PVL is also known as tunnel vision since it makes you feel like you’re in a tiny tunnel. The objects above, below, and around you are black, but everything in front of you is visible.
The patterns of loss, and what each one means
The shape of the loss is diagnostically more informative than its severity, and it tells the clinician roughly where the problem lies before any imaging is done.
Concentric constriction (true tunnel vision), closing in from all sides: advanced glaucoma, retinitis pigmentosa, panretinal laser treatment, vigabatrin toxicity.
Arcuate scotoma or nasal step, an arc-shaped defect curving from the blind spot: the classic early glaucoma pattern, and completely invisible to the person who has it.
A sectoral or wedge-shaped defect in one eye only: branch retinal artery or vein occlusion, retinal detachment, branch of the optic nerve.
Loss of the same side of the field in both eyes (homonymous hemianopia): a lesion behind the optic chiasm, most often stroke, also tumour or trauma. A right-sided field loss indicates a left-sided brain lesion.
Loss of the outer half of the field in both eyes (bitemporal hemianopia): compression at the optic chiasm, classically a pituitary tumour. This pattern requires neuro-imaging and is easily missed, because each eye covers the other’s deficit until the loss is substantial.
Enlarged blind spot: papilloedema from raised intracranial pressure, optic disc drusen.
Altitudinal loss, the upper or lower half of the field in one eye: ischaemic optic neuropathy, branch retinal artery occlusion.
One thing to know about how the field maps onto the eye: the image on the retina is inverted and reversed. A shadow in the upper part of your vision corresponds to a detachment in the lower retina, and loss on the right side of the field corresponds to damage on the left side of the brain.
Peripheral Vision Loss causes
Depending on the reason, PVL might be permanent or transitory. When you get migraines, you may experience temporary PVL. PVL can become permanent due to a variety of factors, including:
Diabetic retinopathy is an eye disease that causes Peripheral vision loss and blindness in diabetics. Vision loss can result from damaged blood vessels in the retina.
Glaucoma refers to a set of eye diseases that affect the optic nerve, resulting in vision loss and possibly blindness. The optic nerve is in charge of delivering impulses to the brain in order to create images.
Retinitis pigmentosa is a set of hereditary diseases that cause your retina to break down and lose cells. This disorder alters the way your retina responds to light, making it more difficult to see.
A typical symptom of a stroke is difficulty seeing in one or both eyes. After a stroke, a person may lose a piece of their peripheral vision. Any vision loss caused by a stroke usually affects both eyes.
Retinal detachment, which produces a progressive shadow or curtain and is a surgical emergency.
Chiasmal compression, most often a pituitary tumour, producing loss of the outer half of the field in both eyes.
Optic neuropathy, including ischaemic, inflammatory, compressive and hereditary forms.
Panretinal photocoagulation (PRP), the laser treatment for proliferative diabetic retinopathy. This deserves specific mention because it is a treatment side effect rather than a disease: PRP deliberately ablates peripheral retina to save central vision, and reduced peripheral field and night vision are the accepted trade-off. Patients are not always told this clearly beforehand, and it is a common source of confusion afterwards.
Medication toxicity, most notably vigabatrin, an anti-epileptic drug that causes irreversible concentric field constriction in a substantial proportion of users and requires formal field monitoring throughout treatment.
Papilloedema from raised intracranial pressure, which enlarges the blind spot and can progress to constriction. Often accompanied by headache, transient greying of vision on standing, and pulsatile tinnitus.
Acute angle-closure glaucoma, which is an emergency and is discussed separately below.
Migraine and transient vision loss
The term "ocular migraine" is used loosely for two different conditions, and separating them matters, because one is common and benign while the other requires investigation.
Migraine with aura is the common one. The disturbance originates in the visual cortex, so it affects both eyes in the same part of the field, even though people often perceive it as coming from one eye. The typical aura is a shimmering zigzag arc that expands across the field over 20 to 30 minutes and then resolves completely, sometimes followed by a headache and sometimes not. It is benign, though frequent new aura in later life warrants review.
Retinal migraine is genuinely monocular, caused by transient vasospasm in the retinal circulation, and it is rare. It is a diagnosis of exclusion, meaning the more dangerous causes of transient monocular vision loss must be ruled out first.
How to tell them apart at home: cover one eye, then the other. If the disturbance is present with both eyes open but disappears when the affected eye is covered, it is monocular. If it persists in the same part of the field whichever eye is covered, it is binocular and cortical. This simple test is genuinely useful and worth remembering.
Why the distinction is important. Transient monocular vision loss, classically described as a curtain descending and then lifting, is amaurosis fugax, and it is the ocular equivalent of a transient ischaemic attack. It is most often caused by an embolus from the carotid artery, and it carries a meaningful risk of a subsequent stroke. It requires urgent assessment, the same day, even though the vision came back. Dismissing it as a migraine is exactly how a preventable stroke gets missed.
Ocular migraines are often mistaken for retinal detachments due to their symptoms of flashes of lights and spots in the vision. Since they are usually for a short period of time and often followed by a migraine headache they are usually easy to differentiate.
In practice the flashes differ in character, which helps: migraine aura is typically a shimmering, geometric, expanding pattern lasting 20 to 30 minutes and affecting both eyes; retinal detachment flashes are brief arcs of light in the peripheral vision, more obvious in dim conditions, in one eye only, and usually accompanied by new floaters. If in doubt, assume detachment and get examined the same day, because the cost of being wrong in that direction is far lower.
Frequent migraines can be a symptom of other health issues and should be followed up with by your doctor.
Diabetic retinopathy and peripheral vision loss
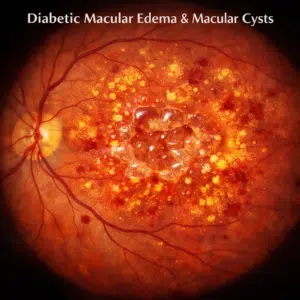
Diabetes can harm the retina’s tiny blood vessels, which supply it. Blood vessels can become leaky as a result of the injury, similar to a water hose with holes in it. Non-proliferative retinopathy is the name for this condition. Fluid escapes from blood vessels into the retinal tissue, potentially causing vision issues. The retina thickens, as a result, resulting in blurred vision.
Blood arteries injured by hyperglycemia (high blood sugar, or high blood glucose) close in another process, triggering a chain of events. When retinal tissue is starved for oxygen it releases vascular endothelial growth factor (VEGF), resulting in the formation of new blood vessels on the retina’s surface. This is called neovascularization. Proliferative retinopathy is a condition in which new blood vessels grow in the retina.
These newly formed blood vessels are fragile and prone to rupturing and bleeding. This causes scar tissue to form on the back wall of the eye, stretching the retina and finally detaching it from the back wall. Retinal detachment is the medical term for this disorder, which can occur suddenly or gradually over time. Specifically this is tractional retinal detachment, in which contracting fibrovascular membranes pull the retina forward without any tear being present. It is a different mechanism from the more common rhegmatogenous detachment described later on this page, and it is managed differently.
How diabetes actually causes peripheral field loss, since the page does not currently make this explicit. Three routes: capillary closure producing patches of non-perfused peripheral retina; tractional detachment; and, importantly, panretinal photocoagulation, the laser treatment for proliferative disease. PRP works by deliberately ablating ischaemic peripheral retina to reduce VEGF production and cause the new vessels to regress. It is highly effective at preventing severe central vision loss, and the cost is reduced peripheral field, poorer night vision and slower dark adaptation. That is a trade most patients would accept, but they should be told about it explicitly, and if peripheral vision has narrowed after laser treatment, that is an expected consequence rather than a sign of failure.
Peripheral vision loss due to glaucoma
Glaucoma can develop for no apparent reason, yet it is influenced by a variety of variables. Intraocular eye pressure is the most essential of these. Your eyes are nourished by a fluid known as aqueous humor. This liquid travels to the front of the eye through the pupil. The fluid exits a healthy eye through a drainage canal called the trabecular meshwork between the iris and the cornea.
To be precise about one thing: raised pressure is the principal modifiable risk factor, not the definition of glaucoma. A substantial proportion of open-angle glaucoma occurs at pressures that never leave the normal range, which is normal-tension glaucoma, and many people with raised pressure never develop glaucoma at all.
One form of Glaucoma causes tiny deposits of pigment that obstruct the drainage canals. Because the fluid has nowhere to go, it accumulates in the eye. This causes the eye pressure to increase. This increased eye pressure can eventually damage the optic nerve, resulting in glaucoma. This describes pigment dispersion glaucoma, which is one specific and relatively uncommon type. It is worth naming rather than presenting as the general mechanism.
In the great majority of cases the problem is outflow resistance, not overproduction. In primary open-angle glaucoma, the most common form, the drainage angle is anatomically open but resistance rises within the trabecular meshwork and the tissue immediately behind it. Genuine overproduction of aqueous humour is uncommon, and presenting it as a main mechanism is misleading, not least because almost every pressure-lowering treatment targets outflow.
How the damage happens is more complex than blood flow being choked off. The leading account is mechanical: pressure stresses the lamina cribrosa, the sieve-like collagen plate that nerve fibres pass through as they leave the eye, disrupting axonal transport and eventually killing retinal ganglion cells. Impaired ocular perfusion is a contributing factor and is thought to be particularly relevant in normal-tension glaucoma, but it is one component rather than the whole mechanism.
Why glaucoma takes peripheral vision first. The nerve fibres serving the mid-peripheral field enter the optic disc at its upper and lower poles, and those are the regions most vulnerable to damage. That anatomy produces the characteristic arcuate scotoma and nasal step patterns, which sit outside the area of attention and are invisible to the person who has them. Central vision is served by fibres entering elsewhere and is typically preserved until very late, which is why someone with advanced glaucoma may still read 20/20 while being unable to move around safely.
Acute angle-closure glaucoma is the emergency exception. Where the drainage angle closes abruptly, pressure rises within hours, producing severe eye pain, a red eye, blurred vision, rainbow haloes around lights, headache, and frequently nausea and vomiting. This requires same-day treatment. Because the nausea often dominates, it is sometimes mistaken for a stomach upset, which delays care.
Vision loss from stroke
Following a stroke, up to two-thirds of persons report vision changes.
According to Stroke.org, up to 66 percent of all stroke survivors will have vision changes as a result of the incident.
After a stroke, vision loss, also known as visual field loss, is frequent.
Stroke victims are thought to have a 20 percent chance of developing a lifelong visual field loss. Hemianopia, Quadrantanopia, and Scotoma are examples of particular forms of visual field loss.
Sudden vision loss can be the first sign of a stroke, and this is the most important sentence in this section. If vision is suddenly lost on one side, or in one eye, treat it as a stroke until proven otherwise and call emergency services. Stroke treatment is time-critical, and eligibility for clot-dissolving treatment depends on how quickly the person is assessed.
A person may have already had a Transient Ischemic Attack, or TIA, before suffering from a stroke. A TIA can cause Peripheral vision loss on either the left or right side of the visual field, with visual field deficits in both eyes being the most common form of visual field deficit following a stroke.
Recovery follows a predictable timeline. Most spontaneous improvement in a post-stroke field defect occurs within the first three to six months, and defects persisting beyond that are usually permanent. Rehabilitation then focuses on compensation rather than recovery: systematic scanning training, and peripheral prisms that shift awareness of objects from the blind side into the seeing field.
Understanding what a homonymous field defect actually is, because the phrase "difficulty seeing in one or both eyes" obscures it. A stroke behind the optic chiasm affects the same side of the visual field in both eyes. Someone with a right homonymous hemianopia cannot see anything to the right of centre, with either eye, and the loss does not change when one eye is covered. That is a completely different pattern from an eye problem, which affects one eye only, and the distinction is what separates a brain cause from an eye cause.
A common consequence worth naming: people with hemianopia frequently collide with door frames and objects on the affected side, and may read only half a page or eat only half a plate without realising, because the missing half does not feel missing. This is visual neglect when it accompanies a right-hemisphere stroke, and it is distinct from the field loss itself.
Driving after a stroke is a serious practical issue: homonymous field loss disqualifies drivers in most jurisdictions, requirements vary by state, and self-reporting obligations often apply. Do not assume driving can resume once you feel recovered.
Tunnel vision from Retinitis Pigmentosa
The loss of night vision is frequently the first sign of retinitis pigmentosa, which appears in childhood. Navigation in low light can be difficult if you have night vision issues. Blind patches form in the side (peripheral) vision as the disease progresses. Tunnel vision develops when these blind patches combine over time. The condition can eventually affect central vision, which is required for precise tasks like reading, driving, and recognizing faces, over years or decades. Many persons with retinitis pigmentosa become legally blind as adults.
Vision loss is most commonly noticed as a child or in early adulthood. The condition worsens over time. The rate of progression varies considerably between the different genetic subtypes, from slow decline over decades to more rapid loss, which is one reason genetic testing has become clinically useful.
The type of retinal cell that is damaged determines the symptoms. The loss of vision in both eyes is common. In the typical rod-cone dystrophy pattern, rods degenerate first, which is why night blindness and mid-peripheral loss come before anything else. Cone-rod dystrophies reverse that order, presenting with central vision loss and light sensitivity first.
It should be mentioned that RP is a condition that progresses slowly over time and that the majority of sufferers never go completely blind. In fact, many patients with RP are regarded as “legally blind” simply because their fields of view are very constricted (poor peripheral vision). Some people still have good central visual acuity.
This is a useful illustration of the second limb of the legal blindness definition: a visual field of 20 degrees or less in the better eye meets the standard regardless of acuity. Someone with RP may read the 20/20 line and be legally blind on field criteria alone.
Symptoms may include the following:
Blindness at night (the most common symptom)
The eyes take longer to adapt to dim illumination or to switch from bright sunlight to indoor lighting.
In foggy or wet conditions, it’s difficult to see.
The term “tunnel vision” refers to a loss of peripheral vision or a narrowing of the visual field.
Colors, especially blue, are difficult to see.
Visual impairment, whether partial or complete, is usually progressive.
Lack of vision causes clumsiness, especially in tight situations like doorways.
Rp is an inherited disease and is passed from one generation to the next. There are no known ways to prevent RP from developing after it has been inherited. If you have RP or a family history of the disorder, you should consult a genetic counselor before starting a family.
Genetic testing has become clinically actionable rather than merely informative. Mutations in more than 100 genes can cause RP, and inheritance may be autosomal dominant, autosomal recessive, X-linked or mitochondrial, which affects the risk to relatives. Voretigene neparvovec is an approved gene therapy for biallelic RPE65-mediated retinal dystrophy, and genotype determines eligibility for a growing number of clinical trials. RP may also occur as part of a syndrome, most commonly Usher syndrome (with hearing loss) and Bardet-Biedl syndrome, and identifying that changes the wider management.
Management otherwise centres on low vision rehabilitation, orientation and mobility training, UV protection, and treating cystoid macular oedema where it occurs, which is a common and treatable cause of additional vision loss in RP that is worth asking about specifically.
Artery and vein occlusions
Blood is carried throughout your body, including your eyes, through arteries and veins. One main artery and one main vein run through the retina of the eye. Branch retinal vein occlusion occurs when the branches of the retinal vein become occluded (BRVO).
Blood and fluid leak out into the retina when a vein is occluded. This fluid might cause the macula to thicken, compromising your central vision. Without blood circulation, nerve cells in the eye can die and eyesight can deteriorate. This also can cause peripheral vision loss symptoms. Depending on how soon it is caught and treated by your eye doctor, lost vision may be permanent vision loss or temporary peripheral vision loss.
Branch retinal artery occlusions can cause sudden peripheral vision loss. Artery and vein occlusions are usually due to underlying medical conditions.
Retinal artery occlusion is a stroke of the eye and is treated as an emergency. Current guidance is that a patient with acute retinal artery occlusion should be assessed urgently in an emergency department for stroke workup, not booked into an eye clinic, because the priority is identifying the embolic source before a cerebral event follows. The usual source is the carotid artery, and a visible cholesterol embolus in a retinal arteriole (a Hollenhorst plaque) is a direct marker of that.
In anyone over 50, giant cell arteritis must be excluded, particularly where there is headache, scalp tenderness, jaw pain on chewing, or unexplained malaise. It requires immediate high-dose corticosteroid treatment to protect the fellow eye and is both sight-threatening and life-threatening.
Both occlusion types are systemic vascular events presenting in the eye. Hypertension, hyperlipidaemia, diabetes and smoking are the principal associations, and open-angle glaucoma is an independent risk factor for vein occlusion. Under the age of 50, thrombophilia and inflammatory screening is warranted. Whatever happens to the vision, the cardiovascular workup is where the patient’s longer-term prognosis actually lies.
Retinal detachments
A retinal detachment is a medical emergency in which a thin layer of tissue at the back of the eye (the retina) is pulled away from its normal location. This condition requires immediate medical attention.
The retinal cells are separated from the layer of blood vessels that gives oxygen and sustenance by a retinal detachment. The longer you wait to treat a retinal detachment, the more likely you are to lose vision in the affected eye permanently.
Symptoms of retinal detachment
Retinal detachment itself is painless. But warning signs almost always appear before it occurs or has advanced, such as:
The sudden appearance of many floaters, tiny specks that seem to drift through your field of vision
Flashes of light in one or both eyes (photopsia)
Blurred vision
Gradually reduced side (peripheral) vision
A curtain-like shadow over your visual field
Macular status is what determines the outcome, and it is why hours matter. A detachment repaired before the macula detaches ("macula-on") frequently retains excellent vision. Once the macula detaches ("macula-off"), final acuity falls substantially and continues to decline with each day of delay. This is the specific reason the symptom triad above warrants same-day examination rather than a routine appointment.
Who is at higher risk: high myopia, previous cataract surgery, blunt eye trauma, lattice degeneration, a detachment in the other eye, and a family history. Most detachments begin with a retinal tear during posterior vitreous detachment, when the vitreous gel separates from the retina, which is itself a common and usually harmless age-related event. That is why new floaters and flashes are worth checking even though most turn out to be benign: examination distinguishes a simple vitreous detachment from one that has torn the retina, and a tear found before it detaches can often be sealed with laser in clinic in a few minutes.
Diagnosis of peripheral vision loss
There are obviously many causes of peripheral vision loss problems. Regular eye examinations are important because they detect field loss early, often years before it would be noticed. They do not prevent it, but early detection is what makes prevention of further loss possible. Diagnosing eye conditions in the early stages is key to maintaining good peripheral sight. Dilated eye exams, visual field tests, and cardiovascular tests all help to determine the underlying causes of peripheral vision loss.
What the tests actually involve:
Confrontation visual fields, a quick bedside screen where the examiner compares your field with theirs. Useful for gross defects, insensitive to subtle ones.
Standard automated perimetry (Humphrey or Octopus), the main quantitative test. You fix on a central target and press a button when you see a light. The key outputs are mean deviation (average sensitivity loss), pattern standard deviation (how uneven the loss is, which distinguishes localised glaucomatous damage from diffuse cataract effect) and, over serial tests, rate of progression, which is what actually drives management. Two baseline tests are usually done because the first is affected by a learning effect.
Goldmann or kinetic perimetry, which maps the far periphery beyond the 30 degrees covered by standard automated testing. Important in retinitis pigmentosa and for driving assessments.
OCT, quantifying retinal nerve fibre layer and macular ganglion cell thickness. Detects structural loss before it becomes measurable on field testing.
Dilated fundus examination, to see the retina and optic nerve directly.
Neuro-imaging, where the pattern suggests a lesion behind the eye, particularly for bitemporal or homonymous defects.
A practical note: visual field testing is tiring and takes practice, and an unreliable first test is common and does not mean something is wrong. Blink normally, keep looking at the central target rather than searching for the lights, and ask for a break if you need one.
Some of the underlying conditions, including diabetes, hypertension and vascular disease, are diagnosed and managed by your primary care physician, and the eye findings often prompt that referral. A healthy diet and lifestyles are so important for not only your body but your eye health also.
Treatment of the loss of peripheral vision
Since there can be so many underlying causes of peripheral vision loss there are many different treatment options. Some may be to treat an underlying medical condition like diabetes or cardiovascular disease. Others may require immediate retinal surgery as in the case of retinal detachment. Glaucoma can be a lifelong ailment that will require drops every day for the rest of your life. However new surgeries are becoming better and a long-term solution. Even though the surgeries may be expensive, the long-term cost of daily medications adds up. Being able to have a procedure and avoid having to do the eye drops daily is quite appealing to many.
Worth adding here that selective laser trabeculoplasty (SLT) now sits between drops and surgery: the LiGHT randomised trial found SLT as first-line treatment achieved comparable disease control to drops with a lower rate of subsequent glaucoma surgery. It is repeatable, and it removes the adherence problem entirely, which matters because real-world persistence with glaucoma drops is poor and the disease gives no feedback when treatment stops.
The most important thing to be clear about: field loss that has already occurred does not come back. Treatment in glaucoma, and in most of the conditions on this page, prevents further loss. That is genuinely valuable, since glaucoma detected and treated early rarely causes disabling vision loss within a lifetime, but it is a different proposition from restoration, and patients are sometimes disappointed when treatment does not improve what they have noticed. Where loss is permanent, rehabilitation is the intervention that changes daily function.
Lifestyle changes for higher-risk people can be one of the best treatment options for visual problems. Diet and exercise reduce blood pressure, can lower blood sugars, all of which make for healthier eyes.
Low vision options for peripheral vision loss
If you happen to be one of the unfortunate people to have permanent peripheral vision loss. There are many devices to help keep you functioning and independent. Glasses with a prism can help with side vision problems. Reverse telescopes are used for tunnel vision in the case of glaucoma and RP. These are just a couple of examples. Be sure to contact one of our low vision specialists to help find the right solutions for you.
Why the usual low vision advice does not apply here. Most low vision content assumes central vision loss and recommends magnification. Magnification is generally unhelpful in peripheral field loss and can make things worse, because enlarging an image spreads it across a field that is already restricted. What helps is the opposite approach: widening awareness, or compressing more of the scene into the field that remains.
Orientation and mobility training is the single most valuable intervention for constricted fields. It covers scanning technique, safe travel strategies, and cane use where appropriate. It is chronically under-referred.
Systematic scanning training, teaching deliberate, structured eye and head movements to compensate for the missing field. Particularly effective after stroke.
Peripheral prisms, such as the Peli prism design, which shift images from the blind area into the seeing field to alert the wearer to obstacles. Mainly used for hemianopia.
Reverse (minifying) telescopes, which compress a wider scene into a constricted field. Useful for spotting rather than continuous wear, and not suitable for everyone.
Lighting and contrast management. Glaucoma and RP degrade contrast sensitivity and dark adaptation disproportionately, so even task lighting, glare control and high-contrast marking of steps, kerbs and door frames make a substantial practical difference.
Falls prevention. Field loss and impaired contrast are established risk factors for falls, so home hazard assessment, stair edge marking, handrails and appropriate footwear belong in the plan. This is one of the highest-value and least glamorous interventions available.
Night vision aids and route planning for people with RP, alongside honest discussion about travelling after dark.
Driving assessment. Field standards apply independently of acuity in every state, and this is the criterion that most often disqualifies people with glaucoma and RP. It is better addressed directly with a low vision specialist than avoided.
Frequently asked questions
Can peripheral vision loss be reversed?
It depends on the cause. Loss from glaucoma, retinitis pigmentosa or completed stroke is generally permanent, and treatment aims to prevent further loss. Loss from retinal detachment can be partly or largely recovered if repaired promptly, particularly before the macula detaches. Loss from migraine aura resolves completely within an hour. Field loss after a stroke may improve spontaneously over the first three to six months. Where loss is permanent, rehabilitation improves function even though the field itself does not change.
Why did I not notice my peripheral vision loss?
Because the visual system actively conceals it. The fellow eye covers what the affected eye misses, and the brain fills in missing areas with surrounding pattern so convincingly that no gap is experienced. Missing field is not seen as blackness; it is simply absent, in the same way you do not perceive an absence behind your head. This is why substantial field loss is frequently discovered on routine examination in someone with no complaints.
Is peripheral vision loss always serious?
The speed of onset is the key. Sudden loss is an emergency until proven otherwise: retinal detachment, stroke, artery occlusion, acute angle closure and giant cell arteritis all present that way and all cause permanent damage within hours to days. Gradual loss over months usually reflects glaucoma or a retinal dystrophy, which need prompt but not emergency assessment. Transient loss lasting under an hour may be migraine aura, but if it affected one eye only it may be amaurosis fugax, which requires same-day assessment because of the stroke risk.
Can you drive with peripheral vision loss?
Sometimes, depending on the extent and pattern. Every state sets a visual field requirement independently of acuity, commonly a horizontal extent of 100 to 140 degrees, and homonymous hemianopia disqualifies drivers in most jurisdictions. Many states also impose self-reporting obligations. Because field standards are separate from acuity standards, passing the chart test tells you nothing about whether you meet them. Check with your state licensing authority and arrange a formal field test.
What is the difference between tunnel vision and blind spots?
Tunnel vision is concentric constriction closing in from all sides, typical of advanced glaucoma and retinitis pigmentosa. A scotoma is a discrete blind area within an otherwise intact field, which can sit anywhere and takes characteristic shapes depending on the cause, such as the arcuate defect of glaucoma. The two are different patterns pointing to different diagnoses.
References
1. Clinical Methods: The History, Physical, and Laboratory Examinations. Chapter on Visual Fields. NCBI Bookshelf, NBK220.
2. Humphrey Visual Field. StatPearls, NCBI Bookshelf, NBK585112.
3. American Academy of Ophthalmology. Primary Open-Angle Glaucoma Preferred Practice Pattern. aao.org.
4. American Academy of Ophthalmology. Posterior Vitreous Detachment, Retinal Breaks, and Lattice Degeneration Preferred Practice Pattern. aao.org.
5. Gazzard G, Konstantakopoulou E, Garway-Heath D, et al. Selective laser trabeculoplasty versus eye drops for first-line treatment of ocular hypertension and glaucoma (LiGHT). *Lancet*. 2019;393(10180):1505-1516.
6. Verbakel SK, van Huet RAC, Boon CJF, et al. Non-syndromic retinitis pigmentosa. *Prog Retin Eye Res*. 2018;66:157-186.
7. Early Treatment Diabetic Retinopathy Study Research Group. Photocoagulation for diabetic macular edema. ETDRS report number 1. *Arch Ophthalmol*. 1985;103(12):1796-1806.
8. Zhang X, Hargitai J, Tosi GM, et al. Peripheral visual field loss after panretinal photocoagulation. *Br J Ophthalmol*. Review.
9. Wild JM, Chiron C, Ahn H, et al. Visual field loss in patients with refractory partial epilepsy treated with vigabatrin. *CNS Drugs*. 2009;23(11):965-982.
10. Biousse V, Nahab F, Newman NJ. Management of acute retinal ischemia: follow the guidelines! *Ophthalmology*. 2018;125(10):1597-1607.
11. Peli E. Field expansion for homonymous hemianopia by optically induced peripheral exotropia. *Optom Vis Sci*. 2000;77(9):453-464.
12. Rowe FJ, Wright D, Brand D, et al. A prospective profile of visual field loss following stroke. *Stroke Res Treat*. 2013;2013:719096.
13. American Academy of Ophthalmology. Vision Rehabilitation Preferred Practice Pattern. aao.org.







 Shop Best Low-Vision Aids with FREE Doctor Consultation.
