



Medically reviewed by Shaun Larsen, OD – Doctor of Optometry, Southern College of Optometry.
Code set: ICD-10-CM FY2026, effective 1 October 2025. | Last reviewed: July 2026 | Next review: October 2026, on release of the FY2027 code set.
Scope: this is a coding and documentation reference for AMD (H35.31– and H35.32–). It covers the full code tables including stage-unspecified and unspecified-eye options, the clinical definitions behind each staging character, the documentation each code requires, and the errors that most often trigger denials. It is not clinical advice, and codes must always be assigned from the physician’s documentation rather than from a summary table.
Quick reference: dry (non-exudative) AMD – H35.31–
Structure: H35.31 [6th character = laterality] [7th character = stage]
6th character – laterality: 1 = right eye, 2 = left eye, 3 = bilateral, 9 = unspecified eye.
7th character – stage: 0 = stage unspecified, 1 = early dry, 2 = intermediate dry, 3 = advanced atrophic without subfoveal involvement, 4 = advanced atrophic with subfoveal involvement.
Right eye: H35.3110 (unspecified), H35.3111 (early), H35.3112 (intermediate), H35.3113 (advanced, no subfoveal), H35.3114 (advanced, subfoveal)
Left eye: H35.3120, H35.3121, H35.3122, H35.3123, H35.3124
Bilateral: H35.3130, H35.3131, H35.3132, H35.3133, H35.3134
Unspecified eye: H35.3190, H35.3191, H35.3192, H35.3193, H35.3194
Quick reference: wet (exudative) AMD – H35.32–
7th character – stage: 0 = stage unspecified, 1 = with active choroidal neovascularisation, 2 = with inactive CNV, 3 = with inactive scar. Note there are four stage values here, against five for dry AMD.
Right eye: H35.3210, H35.3211, H35.3212, H35.3213
Left eye: H35.3220, H35.3221, H35.3222, H35.3223
Bilateral: H35.3230, H35.3231, H35.3232, H35.3233
Unspecified eye: H35.3290, H35.3291, H35.3292, H35.3293
Documentation each code requires
The most common cause of a downcoded or denied AMD claim is documentation that does not support the staging character. To assign a stage other than 0, the record must contain:
Early dry (x1): RPE abnormalities, multiple small drusen (≤ 63 µm), or a few intermediate drusen (> 63 µm and ≤ 124 µm).
Intermediate dry (x2): at least one large druse (≥ 125 µm) or extensive intermediate drusen.
Advanced atrophic without subfoveal involvement (x3): documented geographic atrophy that spares the foveal centre.
Advanced atrophic with subfoveal involvement (x4): geographic atrophy involving the centre of the fovea.
Active CNV (x1): a CNV lesion showing disease activity – intraretinal or subretinal fluid – contributing to visual impairment.
Inactive CNV (x2): a CNV lesion no longer showing activity (no IRF/SRF) that contributes to the patient’s vision loss.
Inactive scar (x3): a CNV lesion that has evolved into a disciform scar causing visual impairment.
Practical point on stage-unspecified codes. The x0 codes exist and are billable, but payers increasingly scrutinise unspecified codes, and for AMD the staging information is normally available in the chart. Query the provider rather than defaulting to x0 where the OCT and examination findings support a specific stage.
Common coding errors and denial triggers
Using bilateral (3) when the stages differ between eyes. The bilateral designation applies when the same stage is present in both eyes. When stages differ, report two codes – one per eye with its own stage.
Confusing the diagnosis code with the treatment eye. Laterality in the diagnosis code describes where the disease is. The procedure code and its modifier (RT/LT) describe which eye was treated. A bilateral diagnosis with unilateral treatment is entirely normal and correct.
Reporting dry and wet AMD in the same eye. An eye is coded as exudative or non-exudative, not both. When one eye converts to wet, that eye takes an H35.32– code; the fellow eye may still carry an H35.31– code.
Failing to update the stage after conversion. An eye previously coded inactive CNV that develops new fluid must move back to the active code. Carrying forward a stale stage from the problem list is a frequent audit finding.
Coding drusen alone as AMD. Small drupelets without other features are not AMD. Consider H35.36 (drusen, degenerative) where the documentation does not support an AMD diagnosis.
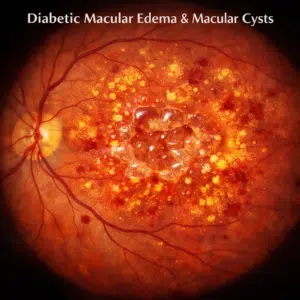
Missing the Excludes note. H35.31– and H35.32– carry an Excludes2 relationship with diabetic retinal disorders (E08.311–E13.359). Where both are present, both may be coded, but the diabetic macular disease is not coded here.
Assuming the code set is static. ICD-10-CM updates each 1 October. Verify against the current fiscal-year files before relying on any published table, including this one.
Clinical background
Your clear, center vision will be lost if you have macular degeneration, an eye condition that predominantly impacts the center part of the retina. The disorder, also known as age-related macular degeneration (AMD), is brought on by the degradation of the macula, a tiny central area of the retina (the inside back layer of the eye).
The macula captures the pictures we view and transfers them from the eye to the brain through the optic nerve. It regulates how well we can read and see small details on items. Images are received blurry as the macula’s cells degenerate.
Macular degeneration does not impair vision in its early stages. However, if the illness develops or reaches its ultimate stages, central vision may be entirely lost. Peripheral vision is characteristically preserved even in advanced AMD – which is why AMD does not cause total blindness, and why patients retain independent mobility while losing the ability to read.
Ophthalmologists who treat patients must be familiar with the many forms of macular degeneration. They are able to count on trustworthy medical coding businesses to accurately record the diagnosis and treatments.
Macular degeneration is the primary, most frequent cause of severe, lifelong vision loss in those aged 60 and older. The ailment, which is more common than cataracts and glaucoma combined, affects around 10 million individuals in the US, according to statistics from the American Macular Degeneration Foundation (AMDF).
AMD often affects both eyes, however, there might be differences in how much each eye is affected. This asymmetry is the reason laterality and stage are coded per eye rather than per patient. Adopting a healthy lifestyle and having routine, thorough eye exams performed by an eye care specialist can help diagnose AMD before the condition results in vision loss. Treatment aims to slow progression and, in neovascular disease, to stabilise or improve vision – anti-VEGF therapy frequently does improve acuity, though vision lost to established subretinal fibrosis does not return.
AMD Types and Stages
Dry AMD
Dry AMD is a kind of AMD that is widespread and is brought on by the macula developing little, yellow protein deposits known as drusen as it ages. Drusen are accumulations of lipid, protein and cellular debris between the retinal pigment epithelium and Bruch’s membrane – they are not blood vessels and they do not leak. About 80% (8 out of 10) of those who have AMD are thought to have the dry variety. The middle portion of your vision may have blind spots with this kind, and if they worsen, you risk losing it altogether.
Wet AMD
Wet AMD is regarded as a less frequent but more dangerous form of the disease and develops when new abnormal blood vessels develop beneath the retina. Your retina is affected by these blood vessels’ leakage of blood and fluid, which distorts your vision. Blood vessel bleeding eventually creates a scar, which results in a permanent loss of central vision. That end state – the disciform scar – is what the H35.32x3 code captures.
Age-related macular degeneration (AMD) has three stages:
Early AMD
People do not feel any form of visual loss at this early stage. Therefore, it is crucial to get frequent eye exams. Defined by medium drusen (63–125 µm) without pigmentary abnormality. Codes to 7th character 1.
Intermediate AMD
AMD at the intermediate stage may cause some degree of vision loss, but there are no other obvious symptoms. At this point, drusen or pigmentary changes in the retina can be found with the assistance of a thorough eye exam. Defined by large drusen (> 125 µm) or medium drusen with pigmentary abnormality. Codes to 7th character 2. This is also the stage at which AREDS2 supplementation has proven benefit, reducing progression risk to advanced disease by approximately 25% – relevant to coding because it is the stage most likely to generate a counselling and monitoring encounter.
Late AMD
Complete visual loss may be apparent at this point. Late AMD takes one of two forms, and they code to different subcategories: geographic atrophy (H35.31x3 or x4) or neovascular disease (H35.32–). "Complete visual loss" overstates it – central vision is severely affected; peripheral vision persists.
Most of the time, people only become aware that they have AMD when their vision gets noticeably hazy. Because an ophthalmologist can identify the causes of early indicators of AMD before a person experiences any vision issues, it is crucial to visit them frequently.
Risk factors and Symptoms
People may not detect any early symptoms or indicators of macular degeneration, as was previously indicated. It’s possible that the problem won’t be detected until the symptoms worsen or both eyes are affected. Some of the typical signs include:
parts of your eyesight that are dark and fuzzy
worsening or lessening of eyesight (Vision may get blurry and it may be difficult for a person to read fine print or drive)
Rarely, color perception might be poorer or different.
Metamorphopsia – distortion, in which straight lines appear bent or wavy. This is the symptom most specific to macular disease and the one most likely to signal conversion to wet AMD. Its omission from the original list is significant, because it is the symptom patients are told to watch for on an Amsler grid.
Difficulty adapting to low light, and needing brighter light to read – often the earliest functional complaint.
It is crucial to see an ophthalmologist as soon as possible if a person exhibits any of these symptoms alone or in combination. New distortion or a new central dark patch warrants assessment within days rather than at the next routine visit, because untreated neovascular AMD progresses over weeks. Age is one of the main risk factors for the illness. Smoking, having a family history of AMD, having high blood pressure, being overweight, and eating a diet heavy in saturated fat are some additional risk factors. Smoking is the strongest modifiable risk factor, associated with roughly two- to four-fold increased risk. Common variants at the complement factor H (CFH) and ARMS2/HTRA1 loci account for much of the heritable component.
Identifying and Treating the Various Forms of AMD
A thorough eye exam, focusing on the retina, will be the first step in the diagnosis of this eye ailment. Drusen, which are microscopic yellow deposits under the retina and are an early indicator of the illness, are something that ophthalmologists will check for.
The ophthalmologist will ask patients to examine an “Amsler Grid” as part of the eye examination. This grid of straight lines, which resembles a checkerboard, helps detect any specific blurry, distorted, or blank places in the patient’s field of vision. It is tested one eye at a time, with reading correction on. It is insensitive, and a normal grid does not exclude progression – it supplements scheduled examinations rather than replacing them.
The retina and macula will also be examined by the ophthalmologist using a special lens to determine whether there have been any changes to them. To enable the ophthalmologist to view the inside of the eye through a specific lens, dilating eye drops could be used to enlarge the pupil. Fluorescein angiography, optical coherence tomography (OCT), and optical coherence tomography angiography are further screening procedures (OCTA). In practice OCT is the study that drives both staging and retreatment decisions, because it detects and quantifies intraretinal and subretinal fluid – the exact findings that separate active from inactive CNV in the 7th character. Fundus autofluorescence is the reference standard for delineating and measuring geographic atrophy, and therefore for distinguishing x3 from x4. Ophthalmologists can start therapy at the appropriate moment with the aid of an early diagnosis.
Treatment differs sharply by form, and the coding follows the clinical distinction.
Non-exudative (dry) AMD. AREDS2 supplementation for intermediate disease or advanced disease in one eye. For geographic atrophy, two complement inhibitors – pegcetacoplan (a C3 inhibitor) and avacincaptad pegol (a C5 inhibitor) – were FDA-approved in 2023 and slow lesion growth; neither demonstrated improvement in visual function in the pivotal trials, both require ongoing intravitreal injection, and reported risks include intraocular inflammation, increased conversion to neovascular AMD, and rare ischaemic optic neuropathy and retinal vasculitis.
Neovascular (wet) AMD. Intravitreal anti-VEGF therapy is standard: bevacizumab (off-label), ranibizumab, aflibercept 2 mg and 8 mg, brolucizumab, and faricimab. Regimens are fixed-interval, treat-and-observe, or treat-and-extend. Photodynamic therapy and thermal laser now occupy narrow niches such as polypoidal choroidal vasculopathy.
Low vision aids, photodynamic laser therapy, anti-angiogenic medications, and laser therapy are all available as treatments. The proper medical codes must be used to precisely document all diagnostic, screening, and therapeutic operations. The right codes on the medical claims may be ensured by using the billing and coding services provided by reputable medical billing and coding firms.
AMD (ICD 10 macular degeneration) Coding for Laterality
You must use the sixth character to indicate laterality when using ICD 10 codes for macular degeneration, dry AMD (H35.31xx), and wet AMD (H35.32xx) as follows:
In the right eye, 1
The left eye, 2
For bilateral, 3
Unspecified eye, 9 – available, but use only where the record genuinely does not identify the eye. Payers scrutinise unspecified laterality.
Tip: Regardless of whether one or both eyes are being treated, use the bilateral designation (3) if the same disease stage is present in both eyes. Where the two eyes are at different stages, do not use the bilateral code – report the right-eye and left-eye codes separately, each with its own stage.
Coding for AMD Dry Staging (dry macular degeneration ICD 10)
The staging is indicated by the seventh character in the dry AMD codes (H35.31xx) as follows:
H35.31x0 for stage unspecified.
H35.31x1 for early dry AMD, which includes abnormalities of the retinal pigment epithelium (RPE), a few tiny drusen (≤ 63 µm), a few intermediate drusen (> 63 µm and ≤ 124 µm), or both.
H35.31x2 for AMD’s dry Intermediate stage – at least 1 large druse (≥ 125 µm) or extensive intermediate drusen (> 63 µm and ≤ 124 µm).
Geographic atrophy (GA) excluding subfoveal involvement in advanced atrophic dry AMD is coded as H35.31x3.
H35.31x4 for subfoveal involvement in advanced atrophic dry AMD – GA affecting the fovea’s center.
Geographic Atrophy: Definition
When does a retina become atrophic? GA is outlined as follows in The Academy Preferred Practice Pattern: The late form of non-neovascular AMD known as central geographic atrophy will have one or more clearly defined zones of RPE and/or choriocapillaris atrophy. The atrophic regions may be surrounded by drusen and other pigmentary abnormalities.
Those with geographic atrophy experience severe visual acuity loss less frequently and more gradually than patients with neovascular AMD. Patients with geographic atrophy, which does not always affect the central fovea, may have relatively high distant visual acuity but exhibit a significantly reduced capacity for close-up tasks like reading. This dissociation is the clinically important point: GA characteristically begins parafoveally and spares the foveal centre until late, so a patient may read a good Snellen line while being functionally unable to read a paragraph, because the letters fall into a paracentral scotoma when tracking a line of text. It is also the reason the x3/x4 distinction exists in the code set. Also possible is choroidal neovascularization. Where that occurs, the eye moves to an H35.32– code.
Geographic Atrophy Coding
The Academy advises indicating if the GA impacts the foveal center when coding: If it does, code H35.31x4; if it doesn’t, code H35.31x3, where “x” denotes laterality. Better categorization of GA will aid clinical management and also result in greater comprehension of the disease’s natural history, comorbidities, and visual prognosis.
Why the GA staging distinction now matters for reimbursement
Researchers and decision-makers will be able to follow the visual impairment and visual function deficiencies that are connected to the disorder with the use of accurate recording and classification. That anticipated situation has now arrived. With pegcetacoplan and avacincaptad pegol approved in 2023 for geographic atrophy secondary to AMD, GA is no longer an untreatable diagnosis coded for registry purposes alone – the H35.31x3 and H35.31x4 codes now support claims for ongoing intravitreal therapy. Accurate subfoveal documentation has moved from academic to financial.
Practical consequence: where a patient is receiving complement inhibitor therapy, the record should document the GA lesion, its foveal relationship, and the imaging (typically fundus autofluorescence) supporting it. Payer policies for these agents are still evolving and vary; verify current coverage criteria and any required prior authorisation with the individual payer.
Prognosis
The risk of vision loss increases when the macula is involved, however even in GA patients without subfoveal involvement, visual function issues might occur. Regarding the prognosis of GA patients, the Academy Basic and Clinical Science Course makes the following observations:
The fovea is frequently spared by GA until the illness is already advanced. Around the fovea, it may first manifest as one or more irregular atrophy patches. The ability to do tasks like reading is hampered by these patches as they expand, consolidate, and may be accompanied by a thick paracentral scotoma. GA patients may have fair visual acuity (VA) until late in the disease’s progression, when the fovea gradually atrophies, causing severe central blindness and necessitating the patient to read and do other visual activities using noncentral retina and eccentric fixation.
A note on eccentric fixation and coding. Where a patient has adapted to using a preferred retinal locus outside the damaged fovea, that adaptation is a rehabilitation outcome rather than a diagnosis, and it does not alter the AMD staging code. It is, however, relevant to low vision service coding and to documenting medical necessity for magnification devices – an area where documentation is frequently thinner than it needs to be.
Staging Coding for Wet AMD (wet macular degeneration ICD 10)
The sixth character of the wet AMD code, H35.32xx, denotes laterality, and the seventh character denotes staging. Note that wet AMD has four stage values (0–3) against five for dry AMD (0–4) – a frequent source of invalid-code errors when staff assume the two subcategories are parallel.
H35.32x0 for stage unspecified.
H35.32x1 for active choroidal neovascularization (CNV), which entails either (1) an AMD-related CNV lesion that exhibits disease activity (i.e., the presence of intraretinal fluid IRF or subretinal fluid SRF) and contributes to the patient’s visual impairment or (2) an AMD-related CNV lesion that does not exhibit disease activity (i.e., no IRF or SRF) in the presence of regular anti-VEGF injections but which shows recurrence of disease activity when anti-VEGF therapy is not given at appropriate intervals.
H35.32x2 for inactive CNV refers to a CNV lesion associated with AMD that no longer exhibits disease activity (i.e., no IRF/SRF) and is a factor in the patient’s vision loss.
An AMD-related CNV lesion that has developed into a disciform scar and is causing visual impairment is described in H35.32x3 for an inactive scar. Given the underlying disciform scar, the CNV lesion may or may not exhibit disease activity (i.e., IRF/SRF), although it is regarded as visually unimportant.
Wet AMD definitions for inactive CNV (H35.32x2) and inactive scar (H35.32x3). The lack of IRF or SRF is what the Academy refers to as “inactive CNV” for the purposes of these ICD-10 classifications. After being diagnosed with inactive CNV, the same eye, however, may develop active CNV, at which point therapeutic options may be considered. When that happens the code must be updated back to x1 – stage is a current-status character, not a historical one. Similarly, an eye with an inactive scar may develop active CNV following the diagnosis of an inactive scar, at which point therapeutic options may be examined.
Related codes you may need alongside AMD
H35.36– – drusen (degenerative) of macula, where documentation does not support an AMD diagnosis.
H35.35– – cystoid macular degeneration.
H35.34– – macular cyst, hole or pseudohole.
H54.– – blindness and low vision categories, frequently required to establish medical necessity for low vision rehabilitation services and devices.
Z83.511 / family history codes – relevant given the strong familial component of AMD.
Procedure side: intravitreal injection (CPT 67028) with the appropriate RT/LT modifier, plus the relevant J-code for the drug administered. OCT (92134) and fundus photography (92250) have their own frequency and documentation rules that vary by payer.
Conclusion
Using the right ICD 10 code for age-related macular degeneration will help ensure proper reimbursement and aid in the documentation of the disease process. It will make it easier to identify what stage the disease is in and which eye or eyes are affected and to what degree.
Frequently asked questions
What is the ICD-10 code for macular degeneration?
There is no single code. Dry (non-exudative) AMD is H35.31– and wet (exudative) AMD is H35.32–, each requiring a 6th character for laterality and a 7th for stage. The three-character stems are not billable – a complete seven-character code is required.
What is the ICD-10 code for dry macular degeneration, bilateral?
H35.313–, completed with the stage character: H35.3130 (unspecified), H35.3131 (early), H35.3132 (intermediate), H35.3133 (advanced atrophic without subfoveal involvement), H35.3134 (advanced atrophic with subfoveal involvement).
What is the ICD-10 code for wet AMD with active CNV?
H35.3211 (right), H35.3221 (left), H35.3231 (bilateral), H35.3291 (unspecified eye).
Is there an ICD-10 code specifically for geographic atrophy?
Not as a standalone code. GA is captured within the dry AMD subcategory as advanced atrophic disease, with the 7th character distinguishing whether the fovea is involved: x3 without subfoveal involvement, x4 with. Given that approved therapies for GA now exist, that distinction carries reimbursement significance.
How do I code when one eye is dry and the other is wet?
Report two codes – an H35.31– code for the non-exudative eye with its stage, and an H35.32– code for the exudative eye with its stage. Do not use a bilateral designation, which would assert the same condition and stage in both eyes.
Sources
1. Centers for Medicare & Medicaid Services / National Center for Health Statistics. ICD-10-CM Official Guidelines for Coding and Reporting, FY2026. cdc.gov/nchs.
2. National Center for Health Statistics. ICD-10-CM FY2026 code files, effective 1 October 2025.
3. American Academy of Ophthalmology. How to use the ICD-10 codes for AMD. *EyeNet*. aao.org.
4. American Academy of Ophthalmology Retina/Vitreous Panel. Preferred Practice Pattern: Age-Related Macular Degeneration. aao.org.
5. Ferris FL, Wilkinson CP, Bird A, et al. Clinical classification of age-related macular degeneration. *Ophthalmology*. 2013;120(4):844–851.
6. Age-Related Eye Disease Study 2 Research Group. Lutein + zeaxanthin and omega-3 fatty acids for age-related macular degeneration: the AREDS2 randomized clinical trial. *JAMA*. 2013;309(19):2005–2015.
7. Heier JS, Lad EM, Holz FG, et al. Pegcetacoplan for the treatment of geographic atrophy secondary to age-related macular degeneration (OAKS and DERBY). *Lancet*. 2023;402(10411):1434–1448.
8. American Academy of Ophthalmology. What to know about Syfovre and Izervay for geographic atrophy. aao.org.






 Shop Best Low-Vision Aids with FREE Doctor Consultation.
